Coronary Stents and Bypass Grafts on CCTA (CAD-RADS 2.0)
David F. Cuevas Cueto, MD · Updated September 27, 2026 · Sources: SCCT 2026 and CAD-RADS 2.0
In a revascularized patient, each stent and each graft is described by its location and patency, and its stenosis is graded on the same scale as native vessels. The definitions follow the SCCT 2026 consensus and CAD-RADS 2.0, which flags stents and grafts with the modifiers S and G and leaves out of the category any stenosis bypassed by a fully patent graft.
Key points
A stent is patent only if contrast opacifies its lumen, because distal contrast can arrive through collaterals.
In-stent restenosis is assessed along the entire stent and at its edges, and it is graded on the same scale as native stenoses.
A nonevaluable stent gives CAD-RADS N if there is no other stenosis of 50% or more, and S is kept, as in N/P2/S.
S and G indicate that stents or grafts are present, do not change the category, and are written in that order, after N, HRP and I.
A stenosis bypassed by a fully patent graft does not count toward the category, but the graft, its distal anastomosis and the distal runoff are graded.
An occluded graft gives CAD-RADS 5, and the native branches proximal to its anastomosis are interpreted again.
Table 1. How stents and grafts count toward the CAD-RADS 2.0 category. Stenosis in a stent or a graft is graded on the native vessel scale, and the patient's category comes from the most severe stenosis that counts.
Situation
How it counts toward the category
Modifier
CAD-RADS 2.0 example
Patent stent
Adds no grade. The category comes from the other lesions.
S
2/P1/S
In-stent restenosis
Graded like a native stenosis (70–99% gives 4A)
S
4A/P3/S
Occluded stent
100%, category 5
S
—
Nonevaluable stent
N replaces the number if there is no other stenosis ≥50%. If there is, N is added as a modifier.
S
N/P2/S
Patent graft
Adds no grade, and the native stenosis it bypasses does not count
G
2/P2/G
Graft stenosis
Graded like a native vessel, at an anastomosis or in the graft body
G
—
Occluded graft
100%, category 5. Native branches proximal to the anastomosis are interpreted again.
G
5/P3/G
Native segment bypassed by a patent graft
Does not count. It is described in the findings.
G (for the graft)
2/P4/G
Source: CAD-RADS 2.0, sections 3.3.2, 3.3.3 and 3.3 (examples of modifier order), Figures 13 and 14; SCCT 2026, pp. 10–12 and Table 5, p. 20.
Also seen as:stent evaluability, non-assessable stent, non-evaluable stent(Spelling used by SCCT 2026 and CAD-RADS 2.0), non-interpretable stent(CAD-RADS 2.0 wording)
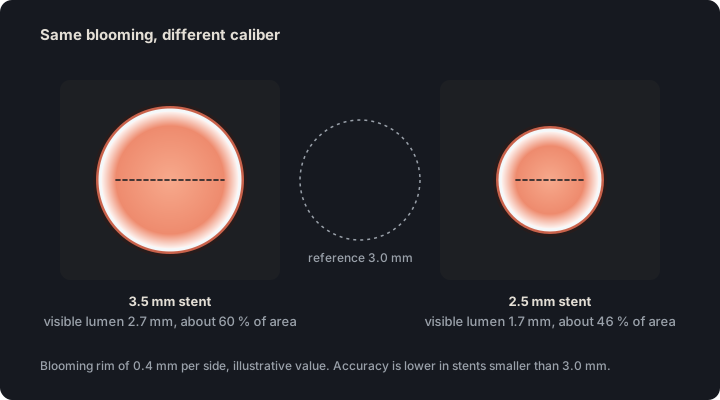
A stent is evaluable when its lumen is seen clearly enough to grade restenosis. If strut blooming, calcium or motion obscures the lumen, the stent is reported as nonevaluable.
How to write it
Proximal LAD stent: nonevaluable; blooming artifact from the struts precludes assessment of the lumen and grading of in-stent restenosis.
Source: SCCT 2026, text on coronary stents (section h), blooming artifact (section e) and Table 5, pp. 10, 15 and 20 · “evaluation of in-stent restenosis (ISR) is highly dependent on stent size, material composition, strut thickness, overlapping segments, overlying dense calcification, and CCTA acquisition and reconstruction protocol”
Details
In practice. Review the stent in cross-sectional and curved planar reformations with a wide window, thin sections and a sharp kernel, or with high-energy virtual monoenergetic images when available. Evaluation depends on the caliber, material and strut thickness of the stent, on overlapping stents, on overlying dense calcium and on the acquisition and reconstruction protocol.
Pitfall. Reporting a small stent as patent when blooming hides its lumen. If the lumen cannot be seen, the stent is nonevaluable and is reported as such.
Other sources. The 2010 appropriate use criteria rated CCTA as inappropriate for evaluating stents smaller than 3 mm or of unknown diameter. SCCT 2026 sets no minimum diameter. (Taylor 2010, cardiac CT AUC, Table 6; SCCT 2026, p. 10)
In CCTA Map
In the stent editor, the “N” button marks the stent as nonevaluable. The template writes “stent nonevaluable for restenosis due to artifact or small caliber” and keeps S. The impression adds a line on the limited accuracy of CCTA for in-stent restenosis in small-caliber stents. “N” also sets aside, without deleting it, any native plaque in the same segment outside the stent: it is no longer described or counted toward the SIS while the N lasts, and it comes back when the N is removed.
Literal output of the map's template
Left anterior descending (LAD): proximal segment: stent nonevaluable for restenosis due to artifact or small caliber; the remainder is unremarkable. Branches D1, D2: no plaque.
Circumflex (LCx): proximal segment: partially calcified plaque causing mild stenosis (25-49%); the rest of the vessel is unremarkable. Branches OM1, OM2, L-PLB: no plaque.
Right coronary (RCA): proximal segment: partially calcified plaque causing minimal stenosis (1-24%); mid segment: partially calcified plaque producing mild stenosis (25-49%); the rest of the vessel is unremarkable. Branches AM, R-PDA, R-PLB: no plaque.
Impression Nondiagnostic study for obstructive CAD. CAD-RADS N/P2/S.
Nonobstructive CAD in LCx and RCA.
CCTA has limited accuracy for in-stent restenosis in small-caliber stents (approximately <3 mm); consider functional imaging or invasive angiography if clinically suspected.
Nonevaluable segments: LAD proximal.
No numeric stenosis grade is assigned: CCTA cannot guide management in this setting and obstructive CAD cannot be excluded. Consider additional or alternative evaluation (repeat CCTA, functional/stress imaging, or invasive angiography).
Figure 1. The same band of blooming covers a larger fraction of the lumen in a small stent. Its thickness is illustrative and depends on the stent, the kernel and the scanner.
Also seen as:stent restenosis, in-stent stenosis, instent restenosis, Mehran classification(four angiographic patterns of restenosis; SCCT 2026 allows adapting it to CT)
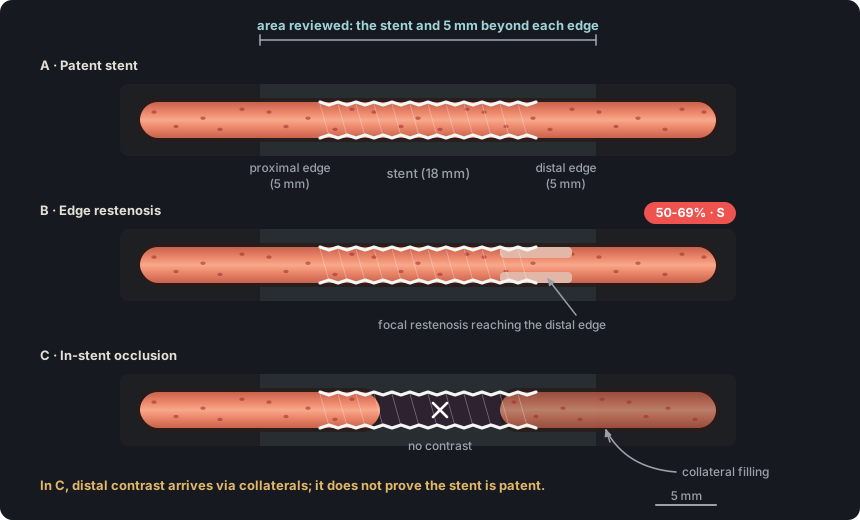
In-stent restenosis is narrowing of the lumen inside the stent or at its edges. SCCT 2026 classifies it as absent, mild (<50%), significant (≥50%), occlusion or nonevaluable. For the CAD-RADS category it is graded on the native stenosis scale, so a significant restenosis can be moderate or severe.
How to write it
Proximal RCA stent: patent, with moderate in-stent restenosis (50–69%).
Do not confuse: Patent means that there is contrast within the stent, not that there is no narrowing: a patent stent can have restenosis.
Source: SCCT 2026, Table 5, interpretation consensus statements (strong recommendation), p. 20 · “In-stent restenosis is classified as absent, mild (<50%), significant (≥50%), occlusion, or non-evaluable.”
Details
In practice. Review the entire stent and its edges in cross-sectional and curved planar reformations, and note whether the restenosis is focal or diffuse and whether it extends beyond the stent edges.
Pitfall. Mistaking the hypodense band that beam hardening leaves next to the struts for neointimal hyperplasia. Review another reconstructed phase before grading restenosis.
Other sources. Invasive angiography uses the Mehran classification, with four patterns. Pattern I is focal, 10 mm or shorter, and pattern II is diffuse but confined to the stent. Pattern III is diffuse and extends beyond the stent edges, and pattern IV is total occlusion. SCCT 2026 states that it can be adapted to CT. (Mehran 1999, Circulation, abstract; SCCT 2026, p. 10)
In CCTA Map
With the “▢ Stent” type, the grade set afterward is the restenosis; choosing “▢ Stent” resets the grade to 0. With the “Severity” buttons, the template writes “mild in-stent restenosis (<50%)” or “significant” with its range, as in “significant in-stent restenosis (50-69%)”, and the category treats it as a native stenosis. Plaque drawn inside the stent is also read as restenosis. Native plaque in the same segment, outside the stent, is described separately as plaque, proximal or distal to the stent. With the “Stenosis grade” slider, it adds the figure to the term and range, as in “significant in-stent restenosis (50-69%; approximately 60%)”.
Literal output of the map's template
Left anterior descending (LAD): proximal segment: significant in-stent restenosis (50-69%); the remainder is unremarkable. Branches D1, D2: no plaque.
Right coronary (RCA): mid segment: partially calcified plaque producing mild stenosis (25-49%); the rest of the vessel is unremarkable. Branches AM, R-PDA, R-PLB: no plaque.
Figure 2. Restenosis is assessed along the entire stent and 5 mm beyond each edge. If the stent lumen does not opacify, distal contrast does not prove patency.
Do not confuse: Contrast in the distal artery does not prove that the stent is patent, because it can arrive through collaterals; patency requires contrast inside the stent.
Source: SCCT 2026, text on coronary stents (section h), p. 10 · “The presence of contrast medium distal to a stent alone is not a definitive sign of patency; contrast opacification should be demonstrated within the stent to establish patency.”
Details
In practice. Follow the lumen on curved planar reformation along the entire stent. The stent is patent if there is contrast proximal to, within and distal to it. The occlusion is reported as total, without assuming it is chronic.
Pitfall. Calling a stent totally occluded when it retains a minimal residual lumen, which can be hard to see. That lumen corresponds to severe restenosis (70–99%), which does not give CAD-RADS 5; occlusion requires no opacification at all.
Other sources. In the interventional literature, chronic total occlusion, including in-stent occlusion, is a 100% stenosis with TIMI 0 flow for more than three months. Because CT cannot establish that duration, the glossary uses "in-stent total occlusion" and does not call it chronic. (Galassi 2019, EuroCTO consensus, Definition and epidemiology)
In CCTA Map
With the “▢ Stent” type at 100%, the template writes "total in-stent occlusion (occluded stent)", the category is 5 and the impression adds a line about the occluded stent.
Literal output of the map's template
Right coronary (RCA): mid segment: total in-stent occlusion (occluded stent); the rest of the vessel is unremarkable. Branches AM, R-PDA, R-PLB: no plaque.
Impression Total occlusion (100%) of at least one vessel. CAD-RADS 5/P1/S.
Obstructive CAD (≥50%) in RCA.
Occluded stent (RCA mid): total in-stent occlusion; the territory depends on native/collateral supply. Correlate with ischemia and assess for reintervention.
S indicates the presence of at least one coronary stent anywhere in the coronary tree. It does not change the category, which is assigned from the most severe stenosis, whether or not it lies within a stent.
Source: CAD-RADS 2.0, section 3.3.2 · “The modifier “S” indicates the presence of at least one coronary stent anywhere in the coronary system.”
Details
In practice. A stent without restenosis adds no grade. Restenosis is graded as a native stenosis, and an occluded stent gives 5. A nonevaluable stent gives N if there is no other stenosis of 50% or more; if there is, that stenosis is graded and N is added as a modifier.
Pitfall. Omitting S because the stent is patent. S indicates the presence of the stent and is written even when there is no restenosis.
Other sources. CAD-RADS 1.0 placed S second, after N, and used V for vulnerable plaque. A patient with a stent and a moderate stenosis with high-risk plaque was coded "3/S/V". CAD-RADS 2.0 replaced V with HRP, added P and places S after HRP and I, as in "3/P3/HRP/S". (CAD-RADS 1.0, section 3.3.5, p. 275; CAD-RADS 2.0, sections 3.3.4 and 3.3)
In CCTA Map
The app adds S as soon as a segment has a “▢ Stent” lesion. The stent does not accept HRP features, and neither does plaque drawn inside it, which is read as restenosis. Native plaque in the same segment, outside the stent, does accept them and can add HRP, as in “CAD-RADS 2/P1/HRP/S”. A stent with no restenosis or other plaque gives CAD-RADS 1/S, a convention specific to the app. With S or G and the “Stable” setting, the suggested management for category 3 proposes CTP or stress testing and notes that CT-FFR is not validated in patients with stents or grafts; if a CT-FFR value has already been entered, it omits that note, and if the code already carries I, it does not propose the test.
Literal output of the map's template
Left anterior descending (LAD): proximal segment: patent stent, no significant restenosis; the remainder is unremarkable. Branches D1, D2: no plaque.
Circumflex (LCx): proximal segment: partially calcified plaque causing mild stenosis (25-49%); the rest of the vessel is unremarkable. Branches OM1, OM2, L-PLB: no plaque.
Right coronary (RCA): mid segment: partially calcified plaque producing mild stenosis (25-49%); the rest of the vessel is unremarkable. Branches AM, R-PDA, R-PLB: no plaque.
Arterial graft (internal mammary and radial artery) LIMA#
Also seen as:left internal mammary artery, LITA(Current anatomical name, left internal thoracic artery), internal thoracic artery graft(Current anatomical name), IMA graft, RIMA(Right internal mammary artery), radial artery graft, arterial conduit
An arterial graft uses one of the patient's arteries as the conduit. The left internal mammary artery is usually left attached to the subclavian artery and anastomosed to the LAD. The radial artery is a free graft.
How to write it
LIMA graft to the mid LAD: patent, without stenosis.
Source: SCCT 2026, text on coronary artery bypass grafts (section i) and beam-hardening artifact (section d), pp. 11 and 15 · “Coronary artery grafts are described by graft type (i.e., arterial or venous), proximal and distal coronary anastomosis sites and distal runoff.”
Details
In practice. Follow the internal mammary graft from the subclavian artery, behind the anterior chest wall, to its anastomosis with the LAD. The metal clips along its course cause beam-hardening artifact, which is reduced with iterative reconstruction or high-energy virtual monoenergetic images.
Pitfall. Mistaking the dark band left by metal clips next to the internal mammary graft for a stenosis. Confirm any stenosis with a wide window and in several planes.
Other sources. Current anatomical nomenclature and many surgical articles call the internal mammary artery the internal thoracic artery, abbreviated ITA. It is the same vessel. The glossary keeps "internal mammary" because it is the SCCT 2026 term, abbreviated LIMA. (IMAIOS e-Anatomy; Taggart 2016, NEJM; SCCT 2026, p. 1)
In CCTA Map
In the “Grafts (bypass)” panel, opened from the “Anatomy ▾” menu, the arterial grafts are “LIMA-LAD” and “Radial-OM2”, and the map draws them with a solid line. The template names the conduit as “left internal mammary artery” or “radial artery”.
Also seen as:vein graft, venous graft, saphenous vein bypass graft, aortocoronary vein graft, greater saphenous vein graft, long saphenous vein graft(Other name for the great saphenous vein), sequential graft, jump graft(supplies several branches in series; SCCT 2026 writes “sequential, jump grafts”)
A vein graft is a segment of the great saphenous vein used as a free graft from the ascending aorta to the coronary artery. When it supplies several branches in series, it is called a sequential graft.
How to write it
Sequential saphenous vein graft from the ascending aorta to OM1 and OM2: patent in both segments, without stenosis.
Source: SCCT 2026, text on coronary artery bypass grafts (section i), pp. 11–12 · “High-density surgical material in the aortic root without adjacent opacified grafts (stump) or random vascular clips around the heart may indicate the presence of a completely occluded graft.”
Details
In practice. Count the grafts and look for each proximal anastomosis on the ascending aorta. In a sequential graft, review each segment, because the occlusion may be limited to one of them.
Pitfall. Missing an occluded graft because it does not opacify. An aortic stump or clips without an opacified graft suggest an occluded graft, and the finding is checked against the operative report.
Other sources. Other texts call the great saphenous vein the greater, long or internal saphenous vein. All four names refer to the same vein, and the glossary uses “great”, the term proposed in 2001 by an international phlebology consensus. (Chen 2009, Australas J Ultrasound Med)
In CCTA Map
The SVG-RCA, SVG-OM, SVG-D1, SVG-D2 and SVG-RI buttons draw saphenous vein grafts as dashed lines. SVG-RI can be turned on only if the map has a ramus intermedius (“Ramus intermedius present”). The template describes the grafts in a separate paragraph, before the native vessels. A graft stenosis set with a button is written with the term and range, as in “patent with moderate stenosis (50-69%)”; with the slider, also with the figure, as in “patent with moderate stenosis (50-69%; approximately 62%)”.
Literal output of the map's template
Coronary bypass grafts (CABG). The following grafts are assessed:
Saphenous vein graft to the OM1: patent with severe stenosis (70-99%; approximately 75%) (body) (SVG-OM).
Circumflex (LCx): proximal segment: partially calcified plaque causing mild stenosis (25-49%); the rest of the vessel is unremarkable. Branches OM1, OM2, L-PLB: no plaque.
Impression Severe obstructive CAD. CAD-RADS 4A/P1/G.
Nonobstructive CAD in LCx.
Graft SVG-OM stenosis (70-99%; approximately 75%): graded like a native vessel (moderate 50-69% / severe ≥70%); correlate with ischemia and assess for revascularization.
Proximal and distal anastomoses, and distal runoff#
Also seen as:distal run-off, run-off vessel(CAD-RADS 2.0 wording), graft anastomosis, end-to-side anastomosis, side-to-side anastomosis(surgical terms; the glossary calls both distal)
The proximal anastomosis joins the graft to its inflow vessel, and the distal anastomosis joins it to the recipient coronary artery. The distal runoff is the native coronary artery supplied by the graft beyond the distal anastomosis.
How to write it
LIMA-LAD graft and distal anastomosis: patent, without stenosis. LAD distal to the anastomosis: severe stenosis (70–99%).
Do not confuse: The bypassed native segment lies proximal to the distal anastomosis and does not count if the graft is fully patent; the anastomosis and the coronary artery distal to it do count toward the category.
Source: SCCT 2026, Table 6, report components (strong recommendation), p. 20 · “Bypass graft (if present) to include type, location, patency, and distal runoff”
Details
In practice. Document the anastomosis sites and their patency, and describe the distal runoff and its stenoses. Lesions beyond the distal anastomosis are easily missed and are sought with thin-slab MIP. With diffuse atherosclerosis, the distal runoff can be difficult to interpret.
Pitfall. Treating a stenosis in the distal runoff as bypassed. CAD-RADS 2.0 evaluates the grafts and the native segments distal to and including the anastomosis. With a LIMA-LAD graft and distal anastomosis without stenosis, a severe stenosis (70–99%) of the LAD distal to the anastomosis, moderate plaque burden (P2), no nonevaluable segment and no other lesion that raises the category, the case is CAD-RADS 4A/P2/G.
Other sources. In the surgical literature, the distal anastomosis is end-to-side when the end of the graft is joined to the side of the coronary artery. In a sequential graft, the intermediate anastomoses are side-to-side. The glossary calls both distal. (Tector 1984, Circulation, abstract)
In CCTA Map
In the graft editor, “Stenosis site” appears if the graft has a stenosis below 100% and offers “Proximal”, “Body” and “Distal”. “Distal” corresponds to the distal anastomosis and is selected by default; the template writes it in parentheses, “(distal)”. With a patent graft (stenosis below 50%), only the native segments proximal to the anastomosis are excluded from the category, and the distal runoff is graded: with a patent LIMA-LAD, a severe distal LAD stenosis gives 4A/P1/G, while one in the proximal LAD is labeled “(bypassed by LIMA-LAD)” and does not count. In the anastomosis segment the reading is per lesion: whatever is drawn entirely before the anastomosis stays bypassed, and the rest is graded. A lesion marked with a single tap on the anastomosis segment has no position and is read as bypassed.
Also seen as:bypassed segment, bypassed native vessel, bypassed native artery
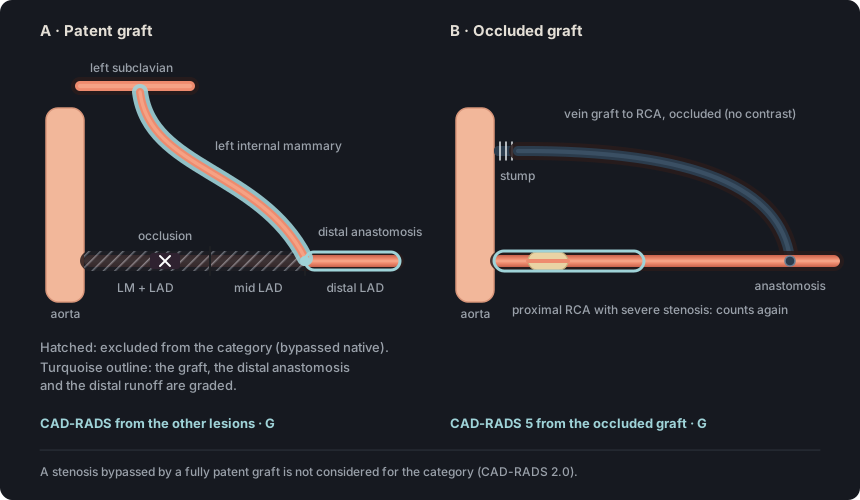
A native segment is bypassed when it lies proximal to the distal anastomosis of a graft. According to CAD-RADS 2.0, a stenosis bypassed by a fully patent graft is not considered for the category.
How to write it
Proximal LAD: total occlusion, bypassed by a patent LIMA-LAD graft.
Source: CAD-RADS 2.0, section 3.3.3 (modifier G) · “A stenosis bypassed by a fully patent graft is not considered for the CAD-RADS classification.”
Details
In practice. The bypassed stenosis is described in the findings, often as an expected occlusion of the native vessel. In that territory, the category takes into account the graft, its distal anastomosis and the coronary artery distal to it.
Pitfall. Continuing to exclude the native vessel when its graft is occluded. If the graft occludes, the native branches proximal to the anastomosis are interpreted and count toward the category.
In CCTA Map
While the graft stenosis is below 50% (a threshold specific to the app), the map excludes from the category the native segments of its target vessel proximal to the anastomosis. Lesions in those segments are labeled, for example, “(bypassed by LIMA-LAD)”, and the impression lists those of 50% or more separately. If the grafted branch arises from a parent vessel that is occluded before its origin, that occlusion is also excluded and labeled, for example, “(retrogradely revascularized via SVG-OM)”. A nonocclusive stenosis of the parent vessel does count. The anastomosis segment is read lesion by lesion, and the distal runoff is graded. A lesion marked with a single tap on the anastomosis segment has no position and is read as bypassed.
Literal output of the map's template
Coronary bypass grafts (CABG). The following grafts are assessed:
Left internal mammary artery graft to the LAD: patent, no significant stenosis (LIMA-LAD).
Left anterior descending (LAD): proximal segment: partially calcified plaque, total occlusion (100%) (bypassed by LIMA-LAD); the remainder is unremarkable. Branches D1, D2: no plaque.
Circumflex (LCx): proximal segment: partially calcified plaque causing mild stenosis (25-49%); the rest of the vessel is unremarkable. Branches OM1, OM2, L-PLB: no plaque.
Right coronary (RCA): mid segment: partially calcified plaque producing mild stenosis (25-49%); the rest of the vessel is unremarkable. Branches AM, R-PDA, R-PLB: no plaque.
Figure 3. With a patent graft, the native stenosis proximal to the anastomosis does not count, but the graft, the distal anastomosis and the distal runoff do. If the graft occludes, it gives CAD-RADS 5 and the native vessel is interpreted again.
Also seen as:occluded graft, bypass graft stenosis, bypass graft occlusion, FitzGibbon classification(angiographic grading of each graft: A, B or O)
Graft stenosis is graded like native-vessel stenosis and is located at an anastomosis or in the graft body. An occluded graft counts as 100% and gives CAD-RADS 5.
How to write it
Saphenous vein graft to OM1: patent, with severe stenosis (70–99%) in the graft body.
Do not confuse: Patent means that the graft lumen contains contrast, not that the graft is free of stenosis.
Source: SCCT 2026, text on coronary artery bypass grafts (section i), p. 11 · “Obstructive disease is described by location (anastomosis site vs. graft body), estimated severity and extent (grading of stenosis similar to native arteries)”
Details
In practice. For each graft, report the site, severity and extent of stenosis. Besides thrombosis and atherosclerosis, a graft can narrow from kinking, tethering or extrinsic compression.
Pitfall. Assigning the category from the native coronary arteries alone when a graft is occluded. Graft occlusion counts as 100% and gives CAD-RADS 5.
Other sources. The angiographic literature uses the FitzGibbon classification, published in 1978, which rates each graft as excellent (A), fair (B) or occluded (O). It assesses both anastomoses and the graft body separately. The glossary instead grades the graft with the CAD-RADS 2.0 percentages. (FitzGibbon 1978, Circulation, abstract)
In CCTA Map
Selecting a graft on the map opens its editor, with the “Severity” buttons and the “Stenosis grade” slider. If there is a stenosis below 100%, “Stenosis site” also appears. The editor has no plaque type, HRP features or “N”. From 25%, graft stenosis is graded like a native-vessel stenosis; from 50% (a threshold specific to the app), the native segments of its target vessel count again. With a button, the template writes the term and range, as in “patent with moderate stenosis (50-69%)”; with the slider it also writes the figure, as in “patent with moderate stenosis (50-69%; approximately 62%)”. A graft with a stenosis also adds to the SIS of the automatic P.
Literal output of the map's template
Coronary bypass grafts (CABG). The following grafts are assessed:
Left internal mammary artery graft to the LAD: patent, no significant stenosis (LIMA-LAD).
Saphenous vein graft to the OM1: patent, no significant stenosis (SVG-OM).
Saphenous vein graft to the RCA: occluded (SVG-RCA).
Left anterior descending (LAD): proximal segment: partially calcified plaque, total occlusion (100%) (bypassed by LIMA-LAD); mid segment: partially calcified plaque resulting in mild stenosis (25-49%); the remainder is unremarkable. Branches D1, D2: no plaque.
Circumflex (LCx): proximal segment: partially calcified plaque causing mild stenosis (25-49%); the rest of the vessel is unremarkable. 1st Obtuse marginal (OM1): partially calcified plaque causing severe stenosis (70-99%) (bypassed by SVG-OM). Branches OM2, L-PLB: no plaque.
Right coronary (RCA): proximal segment: partially calcified plaque causing severe stenosis (70-99%); mid segment: partially calcified plaque producing moderate stenosis (50-69%); the rest of the vessel is unremarkable. Branches AM, R-PDA, R-PLB: no plaque.
Impression Total occlusion of a bypass graft (SVG-RCA). CAD-RADS 5/P3/G.
Obstructive CAD (≥50%) in RCA.
Occluded graft (SVG-RCA): counts as total occlusion in the CAD-RADS category. The territory depends on the native circulation; underlying native disease, if present, is also counted.
Native stenoses bypassed by a patent graft (excluded from the CAD-RADS category): LAD proximal 100% and OM1 severe (70-99%).
Also seen as:G modifier, graft modifier, coronary artery bypass graft(G indicates that there is at least one), CABG(abbreviation of “coronary artery bypass graft”), bypass graft
G indicates the presence of at least one coronary artery bypass graft. Like S, it does not change the category, which is assigned from the most severe stenosis among the grafts, their distal anastomoses, the distal runoff and the non-bypassed native segments.
Source: CAD-RADS 2.0, section 3.3.3 (modifier G) · “The modifier “G” indicates the presence of at least one coronary-artery bypass graft”
Details
In practice. G is written even when all grafts are patent. It goes after N, HRP, I and S, and before E, so a patient with a stent and a graft is coded "…/S/G".
Pitfall. Assigning P from the native coronary arteries alone when the grafts contain plaque. CAD-RADS 2.0 states that total plaque burden should be assessed in both the native coronary arteries and the grafts, and that a combined assessment should be considered when deciding P.
Other sources. In CAD-RADS 1.0, G was the third modifier, before V, and category P did not yet exist. A patent internal mammary graft to the LAD with mild stenoses in the LCx and RCA was coded "2/G". In CAD-RADS 2.0, G comes before E, and a similar case with moderate plaque burden is "2/P2/G". (CAD-RADS 1.0, section 3.3.5, p. 275; CAD-RADS 2.0, sections 3.3.3 and 3.3)
In CCTA Map
G appears as soon as a graft is turned on in the “Grafts (bypass)” panel, opened from the “Anatomy ▾” menu. A graft with no stenosis and no plaque elsewhere gives CAD-RADS 1/G; this is a criterion specific to the app. With G and the “Stable” setting, the suggested management for category 3 proposes CTP or stress testing and notes that CT-FFR is not validated in patients with grafts; if a CT-FFR value has already been entered, it omits that note, and if the code already carries I, it does not propose the test. Grafts with a stenosis add to the SIS of the automatic P, and the report says so with “bypass grafts included”: an SVG-RCA with 50–69% stenosis and no native plaque gives CAD-RADS 3/P1/G. With a patent graft, the runoff distal to the anastomosis does count toward the category; see “Proximal and distal anastomoses, and distal runoff”.
Literal output of the map's template
Coronary bypass grafts (CABG). The following grafts are assessed:
Left internal mammary artery graft to the LAD: patent, no significant stenosis (LIMA-LAD).
Left anterior descending (LAD): proximal segment: partially calcified plaque, total occlusion (100%) (bypassed by LIMA-LAD); the remainder is unremarkable. Branches D1, D2: no plaque.
Circumflex (LCx): proximal segment: partially calcified plaque causing mild stenosis (25-49%); the rest of the vessel is unremarkable. Branches OM1, OM2, L-PLB: no plaque.
Right coronary (RCA): mid segment: patent stent, no significant restenosis; the rest of the vessel is unremarkable. Branches AM, R-PDA, R-PLB: no plaque.
Native stenoses bypassed by a patent graft (excluded from the CAD-RADS category): LAD proximal 100%.
Self-assessment
Short questions to check the key points. The answer appears once you choose an option.
1A stent in the proximal LAD has 60% restenosis. A plaque in the mid RCA causes 30% stenosis, and plaque burden is moderate (P2). What is the CAD-RADS category?
SCCT calls any restenosis of 50% or more significant, but the grade follows the native vessel scale. A 60% restenosis is moderate and gives category 3, and S is added for the stent. See the term
2A stent in the mid RCA shows no contrast in its lumen over a 15 mm segment. The distal RCA and the R-PDA opacify with lower attenuation than the proximal RCA. There is no other stenosis of 50% or more, and plaque burden is moderate (P2). What is the CAD-RADS category?
Distal contrast does not prove that the stent is patent, because it can arrive through collaterals. With no opacification inside the stent, the stent is totally occluded, which counts as 100% and gives category 5. See the term
3A 2.5 mm stent in the mid LAD cannot be assessed because of strut blooming. The proximal LCx and the mid RCA have 30% stenoses, and plaque burden is moderate (P2). How is it coded?
With no other stenosis of 50% or more, the nonevaluable stent prevents assigning a number, and N takes its place. P follows N and S is kept, as in the CAD-RADS 2.0 example. See the term
4A patient has a left internal mammary artery graft to the LAD, with no stenosis in the graft, the anastomosis or the distal runoff. The proximal LAD is occluded, and there are 25–49% stenoses in the LCx and the RCA, with moderate plaque burden (P2). What is the CAD-RADS category?
A stenosis bypassed by a fully patent graft does not count toward the category. The most severe lesion that counts is 25–49%, and G flags the graft. See the term
5The saphenous vein graft to the RCA is occluded. The internal mammary graft to the LAD and the saphenous vein graft to the LCx are patent, and plaque burden is severe (P3). What is the CAD-RADS category?
Total occlusion of a graft counts as 100% and gives category 5, even if the other grafts are patent. G is added because grafts are present. See the term
Rajiah PS, Alkadhi H, Andreini D, Bullock-Palmer RP, Chinnaiyan K, Chow B, et al. Interpretation and reporting of coronary computed tomographic angiography (2026 update): an expert consensus document of the Society of Cardiovascular Computed Tomography (SCCT). J Cardiovasc Comput Tomogr. 2026. doi:10.1016/j.jcct.2026.08.014 Version of record published online in September 2026 under CC BY 4.0, not yet assigned to an issue; cited pages refer to the PDF of this published version.
Cury RC, Leipsic J, Abbara S, Achenbach S, Berman D, Bittencourt M, et al. CAD-RADS 2.0 - 2022 Coronary Artery Disease-Reporting and Data System: an expert consensus document of the SCCT, ACC, ACR and NASCI. J Cardiovasc Comput Tomogr. 2022;16(6):536-57. doi:10.1016/j.jcct.2022.07.002
Koweek L, Achenbach S, Berman DS, Carr JJ, Cury RC, Ghoshhajra B, et al. Standardized medical terminology for cardiac computed tomography 2023 update: an expert consensus document of the SCCT, AAPM, ACR, NASCI and RSNA. J Cardiovasc Comput Tomogr. 2023;17(5):345-54. doi:10.1016/j.jcct.2023.06.002
Narula J, Chandrashekhar Y, Ahmadi A, Abbara S, Berman DS, Blankstein R, et al. SCCT 2021 expert consensus document on coronary computed tomographic angiography: a report of the Society of Cardiovascular Computed Tomography. J Cardiovasc Comput Tomogr. 2021;15(3):192-217. doi:10.1016/j.jcct.2020.11.001
Neves PO, Andrade J, Monção H. Coronary artery calcium score: current status. Radiol Bras. 2017;50(3):182-9.
Tamburino C, Tomasello SD, Capodanno D, Di Salvo ME, Marzà F, Galassi AR. Long-term follow-up after drug eluting stent implantation in left main trifurcations. EuroIntervention. 2009;5(4):432-7. doi:10.4244/eijv5i4a68
Kovacevic M, Burzotta F, Elharty S, Besis G, Aurigemma C, Romagnoli E, et al. Left main trifurcation and its percutaneous treatment: what is known so far? Circ Cardiovasc Interv. 2021;14(3):e009872. doi:10.1161/CIRCINTERVENTIONS.120.009872
Kim C, Park CH, Lee BY, et al. 2024 consensus statement on coronary stenosis and plaque evaluation in CT angiography from the Asian Society of Cardiovascular Imaging-Practical Tutorial (ASCI-PT). Korean J Radiol. 2024;25(4):331-42. doi:10.3348/kjr.2024.0112
Sources for the “Other sources” notes
Cury RC, Abbara S, Achenbach S, et al. CAD-RADS: Coronary Artery Disease – Reporting and Data System. J Cardiovasc Comput Tomogr. 2016;10(4):269-81. doi:10.1016/j.jcct.2016.04.005
Galassi AR, Werner GS, Boukhris M, et al. Percutaneous recanalisation of chronic total occlusions: 2019 consensus document from the EuroCTO Club. EuroIntervention. 2019;15(2):198-208. doi:10.4244/EIJ-D-18-00826
Taylor AJ, Cerqueira M, Hodgson JM, et al. ACCF/SCCT/ACR/AHA/ASE/ASNC/NASCI/SCAI/SCMR 2010 appropriate use criteria for cardiac computed tomography. J Am Coll Cardiol. 2010;56(22):1864-94. doi:10.1016/j.jacc.2010.07.005
Mehran R, Dangas G, Abizaid AS, et al. Angiographic patterns of in-stent restenosis: classification and implications for long-term outcome. Circulation. 1999;100(18):1872-8. doi:10.1161/01.cir.100.18.1872
Taggart DP, Altman DG, Gray AM, et al. Randomized Trial of Bilateral versus Single Internal-Thoracic-Artery Grafts. N Engl J Med. 2016;375(26):2540-9. doi:10.1056/NEJMoa1610021
Chen SS, Prasad SK. Long saphenous vein and its anatomical variations. Australas J Ultrasound Med. 2009;12(1):28-31. doi:10.1002/j.2205-0140.2009.tb00004.x
Tector AJ, Schmahl TM, Canino VR, et al. The role of the sequential internal mammary artery graft in coronary surgery. Circulation. 1984;70(3 Pt 2):I222-5.
FitzGibbon GM, Burton JR, Leach AJ. Coronary bypass graft fate: angiographic grading of 1400 consecutive grafts early after operation and of 1132 after one year. Circulation. 1978;57(6):1070-4. doi:10.1161/01.cir.57.6.1070
This glossary translates and adapts definitions, tables and figures from the SCCT 2026 consensus: Rajiah PS, et al. Interpretation and reporting of coronary computed tomographic angiography (2026 update): an expert consensus document of the Society of Cardiovascular Computed Tomography (SCCT). J Cardiovasc Comput Tomogr. 2026. doi:10.1016/j.jcct.2026.08.014, published under the CC BY 4.0 license. Changes: plain-language rewording and reorganized tables; the diagrams are dynamic schematics of the map and do not reproduce the guideline figures exactly. The SCCT has not reviewed or endorsed this glossary. CC BY 4.0