David F. Cuevas Cueto, MD · Updated September 27, 2026 · Sources: SCCT 2026 and CAD-RADS 2.0
Plaque is described by its composition, by any high-risk features it shows and by the patient's total plaque burden. The definitions follow the SCCT 2026 consensus and CAD-RADS 2.0.
Key points
In calcified plaque, most of the plaque exceeds the attenuation of the contrast-enhanced lumen; non-calcified plaque stays below it, and partially calcified plaque has both components. The reference is the lumen of each study, not a fixed HU value.
The /HRP modifier requires a single plaque to clearly show at least two of the four high-risk features: low attenuation, positive remodeling, spotty calcification and the napkin-ring sign.
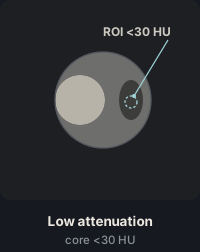
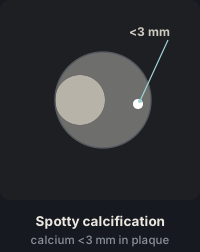
Low attenuation is defined as less than 30 HU, positive remodeling as a remodeling index greater than 1.1 and spotty calcification as a diameter less than 3 mm; the napkin-ring sign has no numeric threshold and is recognized by its shape on the cross-section.
The SIS counts segments with plaque, not plaques: an SIS of 1 to 2 corresponds to P1, 3 to 4 to P2, 5 to 7 to P3, and 8 or more to P4.
The Agatston score is calculated on the non-contrast phase; a score of 0 does not exclude non-calcified plaque, and when such plaque is present, burden is assigned with the SIS.
Plaque burden P1–P4 is independent of stenosis; when methods disagree, the more severe assessment is used, and no P is assigned in CAD-RADS 0.
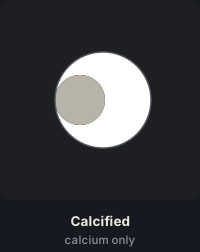
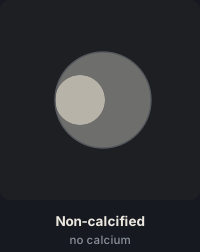
Figure 1. Plaque types in cross-section, in CT grayscale. Calcified plaque exceeds the attenuation of the contrast-enhanced lumen, non-calcified plaque stays below it, and partially calcified plaque combines both components. Legend: contrast-enhanced lumen; non-calcified plaque; low-attenuation core; calcium; peripheral ring; pericoronary fat.
Figure 2. The four high-risk features. The /HRP modifier requires at least two in the same plaque. Positive remodeling is shown in a longitudinal view: the remodeling index is the outer vessel diameter at the lesion divided by the mean of the proximal and distal reference diameters, and it is positive when it exceeds 1.1.
Table 1. Coronary plaque burden classification. The Agatston score is used only if a non-contrast phase was acquired. If methods disagree, CAD-RADS 2.0 directs using the more severe assessment.
Plaque burden
CAD-RADS
Visual assessment
SIS (segments with plaque)
Agatston score
None
No P (CAD-RADS 0)
No plaque
0
0
Mild
P1
1–2 vessels with a mild amount of plaque
1–2
1–100
Moderate
P2
1–2 vessels with a moderate amount, or 3 vessels with a mild amount
3–4
101–300
Severe
P3
3 vessels with a moderate amount, or 1 vessel with a severe amount
5–7
301–999
Extensive
P4
2–3 vessels with a severe amount
≥8
≥1000
Source: Adapted from SCCT 2026 (Rajiah et al.), Table 3, p. 9, CC BY 4.0; the guideline bases it on CAD-RADS 2.0, Table 2. CAD-RADS 2.0 lists ">1000" as the P4 calcium score; SCCT 2026 lists "≥1000".
Also seen as:coronary plaque, coronary artery plaque, atheromatous plaque, coronary atheroma(usual term in intravascular imaging; CCTA uses “plaque”; SCCT 2024 quantification, section 3)
On CCTA, atherosclerotic plaque is tissue in the vessel wall, between the contrast-enhanced lumen and the outer vessel contour, that can be distinguished from the lumen and from pericoronary fat. For visual reading and semiquantitative burden scores such as the SIS, the SCCT 2024 quantification document keeps the traditional definition, which also requires an area of at least 1 mm² and identification of the tissue in at least two independent planes.
How to write it
Proximal and mid LAD: diffuse partially calcified plaque with mild maximal stenosis (25–49%) in the mid LAD.
Do not confuse: Plaque is tissue in the wall; stenosis is the reduction in luminal diameter relative to a normal reference segment, not relative to the outer wall at the plaque. A plaque with positive remodeling may not narrow the lumen, and a narrowing without plaque, such as that of an anomalous artery with an interarterial course, is graded in the same way and carries E.
Source: SCCT 2024 quantification, section 4 and Table 2; SCCT 2026, coronary interpretation, atherosclerotic plaque, stenosis and interpretation pitfalls, pp. 2, 4, 5–7 and 15–18; CAD-RADS 2.0, section 3.3.6 and Table 4, note b; Karlo 2012, sections on evaluation and on false-positive findings · “presence of tissue structures ≥1 mm² within or adjacent to the coronary artery lumen”
Details
In practice. Each segment is reviewed on axial images, thin-slab MIP and oblique and curved MPR. A suspected plaque is confirmed in two planes: on cross-sectional views perpendicular to the centerline, which best show its size and composition, and in a longitudinal plane. The window is adjusted to separate the contrast-enhanced lumen from calcium, and non-calcified plaque from the myocardium and from pericoronary fat, whose interface generally marks the outer vessel contour. If an artifact is suspected, another phase is reviewed: a true plaque is seen in both and is separated from the adjacent tissue along its entire contour.
Pitfall. Calling something plaque when it is seen in only one plane or one phase. The opposite error also occurs: on axial images, a non-calcified plaque can be mistaken for partial volume or go unnoticed if its attenuation resembles that of pericoronary fat, and a small calcified plaque can have the same attenuation as the lumen. An unexplained change in caliber calls for another look at the segment, and the non-contrast series helps to show calcium.
Other sources. The 2024 SCCT quantification document notes that CCTA does not usually detect plaques less than 500 µm thick. The SCCT 2023 terminology does not define plaque itself, only its three types. (SCCT 2024 quantification, section 2.3; SCCT 2023 terminology, Table 4)
Artifacts and findings that mimic or hide plaque, and how to tell them apart.
Mimic
What it does to plaque
How to tell it apart
Motion
High- or low-attenuation streaks that are mistaken for calcified or non-calcified plaque; the blurring can also hide a true plaque
Another reconstructed phase: a finding seen in only one phase suggests artifact, and a true plaque is separated from the adjacent tissue along its entire contour
Misalignment between slabs
A step that mimics a lesion; a portion of the vessel may be missing or duplicated, and plaque is underestimated or overestimated
Another phase, or turning off edge correction
Partial volume averaging
Pseudostenosis at the boundary between slabs, and overestimated stenosis at bifurcations and in tortuous segments; on axial images, a non-calcified plaque can be mistaken for partial volume
Orthogonal and curved MPR or thin-slab MIP; at the slab boundary, another phase or turning off edge correction
Blooming (calcium or stent)
Calcified plaque looks larger and stenosis is overestimated
A hypodense band next to calcium or a stent that mimics non-calcified plaque or in-stent hyperplasia; it can also hide a true non-calcified component
It arises from calcium or metal, may improve in another phase and decreases with higher-level iterative reconstruction or high-energy virtual monoenergetic images
Suboptimal enhancement or contrast mixing
A low-density lumen that mimics non-calcified plaque or stenosis
Other phases, another window and thicker slices; a true plaque thickens the wall
Wall thickening of vasculitis
May be mistaken for atherosclerotic plaque
Smooth, enhancing thickening that is circumferential or continuous with stranding of the adjacent fat suggests vasculitis; it is not plaque: it is described separately and carries E
Source: SCCT 2026, pp. 13–18, and Table 4, p. 15; SCCT 2024 quantification, section 2.2; Karlo 2012, section on false-positive findings; Woodworth 2024, abstract; CAD-RADS 2.0, section 3.3.6
In CCTA Map
Plaque is recorded as a lesion of the segment. It is marked by tapping a vessel or dragging along it, and in the editor that opens the user chooses the “Severity” (buttons 0 to 5, from “normal” to “100%”), the “Plaque type” (“Calcified”, “Partly calc.” or “Noncalcified”) and the high-risk “Flags”. A dragged stroke starts as “Partly calc.” with minimal stenosis, and the map also saves a grade above 0 with no type as “Partly calc.” plaque. A lesion at “normal” counts as plaque only if a type has been chosen: the summary then shows “Plaque: Detected”, the segment counts toward the SIS and, if no other lesion has a grade, the category changes from CAD-RADS 0 to 1. The map does not record in which planes or phases the plaque was confirmed. A narrowing without plaque is marked with the “Non-atherosclerotic” type: it is graded, adds E and does not count as plaque in the SIS or P. A plaque at 0% is written with its type, as in “non-calcified plaque without significant stenosis”.
Also seen as:calcific plaque, hard plaque(suggests a mechanical property that CT does not assess; SCCT 2024 quantification, section 4.1)not recommended
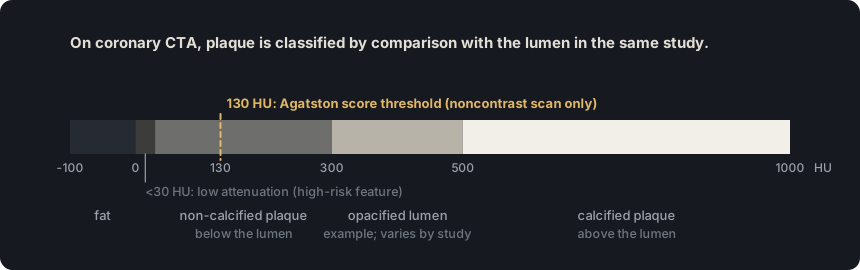
In SCCT 2026, which this glossary follows, a plaque is calcified if most of its volume has higher attenuation than the opacified lumen. The criterion is relative to the vessel lumen, not a fixed HU threshold.
How to write it
Proximal LAD: dense calcified plaque with moderate stenosis (50–69%); the stenosis grade may be overestimated because of blooming artifact.
Do not confuse: Calcified plaque is not the same as a nonevaluable segment: if the lumen can be assessed, report the highest visible grade with the blooming caveat; the segment is nonevaluable when the artifact prevents confident assessment of the lumen.
Source: SCCT 2026, section on atherosclerotic plaque, p. 5 · “(largely) calcified plaque: attenuation values of most of the plaque exceed the values of the contrast-enhanced blood”
Details
In practice. Assess it on cross-sections perpendicular to the vessel axis, with a wide window and, when available, a sharper kernel to reduce blooming. With dense calcium, report the highest visible grade and note that it may be overestimated.
Pitfall. The 130 HU Agatston threshold does not define calcified plaque on CTA. The reference is the attenuation of the opacified lumen.
Other sources. In semi-automated plaque quantification, most software classifies tissue above 350 HU as dense calcium. The SCCT 2023 terminology defines calcified plaque by an attenuation of the entire plaque consistent with calcium; the glossary follows the SCCT 2026 visual criterion, which uses the contrast-enhanced lumen as the reference and requires most of the plaque to exceed it. (SCCT 2024 quantification, section 4.2; SCCT 2023 terminology, Table 4)
In CCTA Map
In the lesion editor, selecting “Calcified” as the plaque type disables “Low attenuation” and “Napkin-ring sign” and removes those two features if the plaque already had them. If the stenosis is 50–99%, the template adds a caveat to both the findings and the impression that the grade may be overestimated by calcium blooming. The “N” button sets the segment’s plaque aside without deleting it: the segment is reported as nonevaluable, and the plaque comes back when the N is removed. With “Describe visible plaque”, the report names it without grading the stenosis. Plaque set aside does not count toward the SIS.
Literal output of the map's template
Left anterior descending (LAD): proximal segment: calcified plaque causing moderate stenosis (50-69%), grade possibly overestimated by calcium blooming; the remainder is unremarkable. Branches D1, D2: no plaque.
Dense calcification may overestimate the stenosis grade (blooming artifact); if management depends on the grade, consider CT-FFR or functional testing.
Figure 3. Plaque composition is judged against the lumen attenuation of each study. The 130 HU threshold belongs to the Agatston score, which is calculated on the non-contrast phase.
Also seen as:mixed plaque(SCCT 2023 terminology, Table 4; SCCT 2024 quantification, section 4.1)not recommended, partially non-calcified plaque(SCCT 2014 term)
It combines a calcified and a non-calcified component. The SCCT uses this term rather than "mixed plaque". If one component makes up at least 75%, it can be called predominantly calcified or predominantly non-calcified.
Source: SCCT 2026, section on atherosclerotic plaque, p. 5 · “partially calcified: with both calcified and non-calcified components (Fig 6). A partially calcified plaque can be specified as predominantly calcified with ≥ 75 % of the plaque component calcified”
Details
In practice. Review it on cross-sections and on multiplanar reformats, which help separate the non-calcified component from pericoronary fat. Plaque type is recorded for each segment; predominance is an optional qualifier in the text.
Pitfall. A plaque can be mistaken for calcified when beam hardening next to the calcium hides its non-calcified component. Review it with a wide window and in several planes.
Other sources. SCCT 2014 called it “partially non-calcified” and listed “predominantly calcified” and “predominantly non-calcified” separately, without a percentage threshold. Several articles call it “mixed plaque”, a term the SCCT 2023 terminology lists as not recommended and the 2024 SCCT quantification document also discourages. (SCCT 2014, section 10.6.2; SCCT 2023 terminology, Table 4; SCCT 2024 quantification, section 4.1)
In CCTA Map
In the editor it is marked with the “Partly calc.” button and accepts all four high-risk features. The template describes it as "partially calcified plaque".
Also seen as:noncalcified plaque, NCP, soft plaquenot recommended, lipid plaquenot recommended, lipid-rich plaque(SCCT 2026, p. 5; SCCT 2024 quantification, section 4.1)not recommended, fibrous plaquenot recommended, fibro-fatty plaque(suggests a histology that CT does not assess; SCCT 2024 quantification, section 4.1)not recommended
Non-calcified plaque has lower attenuation than the opacified lumen. The SCCT recommends this term instead of "soft" or "lipid-rich".
How to write it
Proximal LAD: non-calcified plaque without visible luminal narrowing.
Do not confuse: “Without visible luminal narrowing” corresponds to 0% in CAD-RADS 2.0 (“No visible stenosis”). “Without significant stenosis” is not a grade on the scale: it does not state whether the lumen is narrowed or by how much.
Source: SCCT 2026, section on atherosclerotic plaque, p. 5 · “non-calcified plaque: attenuation values of the plaque are below the values of the contrast-enhanced blood”
Details
In practice. In addition to axial images, look for it on orthogonal and curved multiplanar reformats, because on axial images it can be missed or mistaken for a partial volume effect. It can also be confused with pericoronary fat. An unexplained change in caliber should prompt a closer look at the segment.
Pitfall. Calling it "soft" or "lipid" plaque is imprecise, because its attenuation depends on tube voltage and lumen opacification and does not predict histology in an individual patient.
Other sources. Quantification software subdivides non-calcified plaque by HU ranges with names such as fibrous, fibro-fatty or necrotic core. Thresholds and names vary between vendors, and SCCT 2024 discourages calling it "fibrous". (SCCT 2024 quantification, sections 4.1 and 4.2, Fig. 3)
In CCTA Map
It is marked with the “Noncalcified” button under “Plaque type” in the editor, and the template describes it as “non-calcified plaque” in its segment. A plaque marked at 0% is written with its type, “non-calcified plaque without significant stenosis”, and when a segment has several plaques, the template names them all, from the highest grade down, with “in the same segment, another…”.
Also seen as:high-risk plaque features, vulnerable plaque(replaced by HRP in CAD-RADS 2.0; SCCT 2024 quantification, section 4.1)not recommended, V modifier(CAD-RADS 1.0; replaced by HRP in CAD-RADS 2.0)not recommended, vulnerable plaque featuresnot recommended, adverse plaque features(SCCT 2023 terminology, Table 4)not recommended, adverse plaque(SCCT 2023 terminology, Table 4; in SCOT-HEART one feature was enough)not recommended
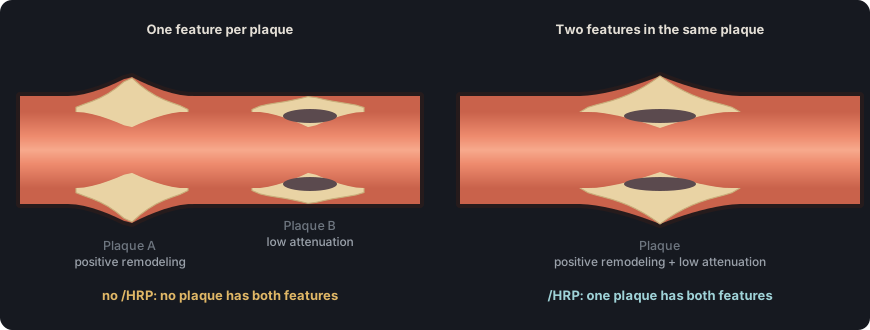
In CAD-RADS 2.0, a plaque is high-risk if it clearly shows at least two of four features (low attenuation, positive remodeling, spotty calcification and the napkin-ring sign). It is flagged with the /HRP modifier.
How to write it
Mid RCA: non-calcified plaque with mild stenosis (25–49%) and two high-risk plaque features: low attenuation and positive remodeling.
Do not confuse: A single high-risk feature can be described in the findings but does not warrant /HRP: the modifier requires at least two clearly present features in the same plaque.
Source: CAD-RADS 2.0, section 3.3.4 and Figure 15 · “If a coronary plaque clearly demonstrates two or more high-risk features by CCTA, the modifier “HRP” (high risk plaque) should be added”
Details
In practice. Review each plaque on cross-sections and count its features. If it has two or more, add /HRP to the category and name the features in the findings.
Pitfall. Features from different plaques are not added together to reach two. The modifier requires the features to be in the same plaque.
Other sources. CAD-RADS 1.0 used the “V” (vulnerability) modifier with the same two-or-more criterion; CAD-RADS 2.0 replaced it with “HRP”. In SCOT-HEART, “adverse plaque” was defined by positive remodeling or low attenuation; one of them was enough. The SCCT 2023 terminology does not recommend the terms “vulnerable plaque features” or “adverse plaque features”, and the 2024 SCCT quantification document discourages “vulnerable plaque”. (CAD-RADS 1.0, section 3.3.4; CAD-RADS 2.0, section 3.3; Williams 2019, SCOT-HEART; SCCT 2023 terminology, Table 4; SCCT 2024 quantification, section 4.1)
In CCTA Map
The four features are listed under “Flags” in the editor of each lesion, with an “HRP n/4” counter that counts the features of that plaque and shows ⚠ once it reaches two. Features are stored per plaque: the /HRP modifier appears when a single plaque has two or more, and two plaques with one feature each do not trigger it, even in the same segment. A plaque drawn with a single stroke across two segments counts as one plaque and carries the same features in both. If a plaque has a single feature, the template describes it as an isolated feature of that plaque.
Literal output of the map's template
Left anterior descending (LAD): proximal segment: non-calcified plaque causing mild stenosis (25-49%) with high-risk plaque features (low attenuation and positive remodeling); the remainder is unremarkable. Branches D1, D2: no plaque.
Right coronary (RCA): mid segment: partially calcified plaque producing mild stenosis (25-49%) with spotty calcification as an isolated feature; the rest of the vessel is unremarkable. Branches AM, R-PDA, R-PLB: no plaque.
Figure 4. The /HRP modifier requires two features in the same plaque. Two plaques with one feature each do not trigger it; the features are described in the findings.
Also seen as:LAP, low-attenuation non-calcified plaque, low-density plaque(the glossary uses “attenuation”, as the SCCT does)avoided in this glossary
In CAD-RADS 2.0 and SCCT 2026, a non-calcified plaque has low attenuation, one of the high-risk features, when its internal attenuation is less than 30 HU. The measured value depends on tube voltage and lumen opacification.
How to write it
Proximal LCx: low-attenuation non-calcified plaque with mild stenosis (25–49%).
Do not confuse: Not every non-calcified plaque has low attenuation: in CAD-RADS 2.0, the feature requires the internal attenuation of the non-calcified component to be below 30 HU.
Source: CAD-RADS 2.0, Figure 15; SCCT 2026, p. 5 · “Low attenuation plaque, defined as non-calcified plaque with internal attenuation less than 30 HU.”
Details
In practice. Measure it on the cross-section with a small region of interest placed in the most hypodense part of the plaque, away from the lumen, calcium and pericoronary fat. Keep the acquisition tube voltage in mind.
Pitfall. Measuring next to dense calcium or at the border with pericoronary fat gives falsely low values, from beam hardening and partial volume.
Other sources. In volumetric quantification, the upper limit of the lowest-attenuation category ranges from 30 to 75 HU across vendors, and SCCT 2024 sets no absolute threshold. The glossary follows CAD-RADS 2.0. (SCCT 2024 quantification, section 4.2)
In CCTA Map
It is marked with the “Low attenuation” button in the editor, which is disabled when the plaque type is “Calcified”.
Also seen as:PR, positive remodelling, outward remodeling, expansive remodeling, compensatory enlargement(Glagov 1987)
In CAD-RADS 2.0 and SCCT 2026, positive remodeling is present when the outer vessel diameter at the plaque is more than 10% larger than the reference diameter (remodeling index greater than 1.1). It is a high-risk feature.
How to write it
Proximal LAD: non-calcified plaque with positive remodeling, without visible luminal narrowing.
Do not confuse: Positive remodeling without luminal narrowing is not CAD-RADS 0: CAD-RADS 2.0 places plaque with positive remodeling and no evidence of stenosis in category 1.
Source: CAD-RADS 2.0, Figure 15; SCCT 2026, p. 5 · “Positive remodeling, defined as the ratio of outer vessel diameter at the site of plaque divided by the average outer diameter of the proximal and distal vessel greater than 1.1”
Details
In practice. On cross-sections, measure the outer vessel diameter, from outer wall border to outer wall border, at the plaque and at healthy proximal and distal reference segments. The index is the diameter at the lesion divided by the mean of the two reference diameters.
Pitfall. Using the lumen instead of the outer vessel contour to calculate the index is an error. Likewise, stenosis is graded against normal reference segments, not against the remodeled wall.
Other sources. The SCCT 2024 quantification document calculates the index with vessel areas, not diameters; it considers it positive at 1.10 or higher and negative below 0.90. The glossary uses diameters, as CAD-RADS 2.0 does. (SCCT 2024 quantification, Table 2)
In CCTA Map
It is marked with the “Positive remodeling” button in the editor, which remains available even when the plaque type is “Calcified”.
Source: SCCT 2026, section on atherosclerotic plaque, p. 5 · “Features of high-risk plaque (HRP) include positive remodeling (outer vessel diameter >10% larger than the reference diameter), spotty calcification (diameter <3 mm)”
Details
In practice. Measure the largest diameter of the deposit on the cross-section and the curved reformat, with a wide window to limit blooming. If it measures 3 mm or more, it no longer meets the criterion.
Pitfall. A small, isolated calcified plaque is not spotty calcification. The feature describes a calcium focus smaller than 3 mm within a plaque.
Other sources. Some authors define it relative to the vessel: its length is less than 1.5 times the vessel diameter and its width less than two-thirds of that diameter. The glossary follows the 3 mm limit of SCCT 2026. (van Rosendael 2024, Table 1; Yang 2021, Methods)
In CCTA Map
In the editor it is marked with the “Spotty calcification” button, and the template describes it as "spotty calcification".
Also seen as:NRS, napkin ring sign, ring-like sign, ring-like enhancement(used in some studies)
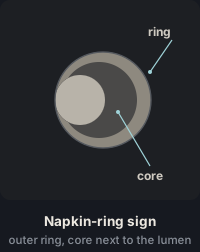
The napkin-ring sign is a high-risk feature seen on the cross-section of a non-calcified plaque: a low-attenuation center, apparently in contact with the lumen, surrounded by a ring of higher attenuation.
How to write it
Proximal LAD: non-calcified plaque with a napkin-ring sign and moderate stenosis (50–69%).
Source: SCCT 2026, section on atherosclerotic plaque, p. 5 · “napkin-ring sign (central low attenuation apparently in contact with the lumen surrounded by ring-like higher-attenuation plaque tissue)”
Details
In practice. Look for it on cross-sections perpendicular to the vessel centerline, with a window setting that clearly separates the attenuation levels within the plaque. The ring is non-calcified tissue that is denser than the center; it is not calcium.
Pitfall. It can be mimicked by the calcified rim of a partially calcified plaque and by partial volume artifact at the plaque–lumen interface.
Other sources. Some reviews specify that the peripheral ring does not exceed 130 HU, and some studies call it ring-like enhancement. The 2024 SCCT quantification consensus states that the sign does not require measuring attenuation. (van Rosendael 2024, Table 1; Pozo 2016; SCCT 2024 quantification, section 4.1)
In CCTA Map
The editor records it with the “Napkin-ring sign” button, which is disabled when the plaque type is “Calcified”.
Also seen as:CAD-RADS plaque burden, total plaque burden, overall plaque burden, atherosclerotic burden, P modifier(CAD-RADS 2.0 calls it the P category and keeps it separate from the modifiers)avoided in this glossary
In CAD-RADS 2.0, which this glossary follows, plaque burden is the patient's overall amount of coronary plaque, independent of the stenosis grade. It is expressed as P1 (mild), P2 (moderate), P3 (severe) or P4 (extensive), based on the SIS, the Agatston score or visual assessment.
How to write it
Coronary atherosclerosis with severe plaque burden (P3; SIS 5); the maximal stenosis is mild (25–49%). CAD-RADS 2/P3.
This example assumes: All segments larger than 1.5 mm are evaluable, no other method gives a higher P (if one does, use the most severe assessment), and no modifier applies; with a nonevaluable segment, write CAD-RADS N/P3, or N without P if the overall plaque assessment is not reliable.
Do not confuse: Plaque burden (P1–P4) summarizes how much plaque there is in the whole coronary tree; the stenosis category (0–5) comes from the most severe stenosis. A P3 burden with mild maximal stenosis is still CAD-RADS 2.
Source: SCCT 2026, text and Table 3, pp. 7 and 9; CAD-RADS 2.0, section 3.2.1 · “CAD-RADS 2.0 introduces the P1 to P4 descriptors which are used to denote increasing categories of plaque burden (P1=mild, P2=moderate, P3=severe and P4=extensive)”
Details
In practice. SCCT 2026 recommends estimating burden visually and combining that estimate with the Agatston score, if acquired, or with the SIS. If several methods are applied, CAD-RADS 2.0 directs using the most severe assessment. No P is assigned in CAD-RADS 0, and with N it is assigned only if the overall plaque assessment is reliable.
Pitfall. With abundant non-calcified plaque, P should not be assigned from the Agatston score alone, because burden would be underestimated; in that case, assign P from the SIS or visual assessment.
Other sources. In CT plaque quantification, "plaque burden" also refers to the percentage of vessel area or volume occupied by plaque. The glossary uses it as CAD-RADS 2.0 does, for the patient's overall amount of plaque. (SCCT 2024 quantification, Table 2)
In CCTA Map
In the “Plaque burden (P)” section of the “Modifiers P · I ▾” panel, P comes from one of three sources: “Auto (map)”, which uses the SIS counted on the map; “Calcium (Agatston)”, which uses the score you enter; or “Pick P”, which sets it manually or leaves it empty with “—”. The template prints, for example, “Plaque burden: mild (P1; SIS 2).” With N, whether from a marked segment or from the “nondiagnostic” option in the “Quality” selector, the map still prints the P given by the chosen mode; if the overall plaque burden cannot be assessed reliably, remove it by choosing “—” under “Pick P”. Each mode uses a single source. With Agatston 0 and plaque on the map, P comes from the SIS with the note “P by SIS (Agatston 0 does not reflect non-calcified plaque)” in the P panel, and the report says only “(P by SIS)”; with an Agatston score above 0, P comes from calcium even if the SIS gives a higher band, a decision still pending with the author. Grafts with a stenosis add to the SIS, and the report says so with “bypass grafts included”. Plaque set aside by N does not count toward the SIS.
Literal output of the map's template
Plaque burden: severe (P3; SIS 5).
Left main (LM): calcified plaque resulting in minimal stenosis (1-24%).
Left anterior descending (LAD): proximal segment: calcified plaque causing minimal stenosis (1-24%); mid segment: partially calcified plaque resulting in mild stenosis (25-49%); the remainder is unremarkable. Branches D1, D2: no plaque.
Circumflex (LCx): proximal segment: calcified plaque causing minimal stenosis (1-24%); the rest of the vessel is unremarkable. Branches OM1, OM2, L-PLB: no plaque.
Right coronary (RCA): proximal segment: calcified plaque causing minimal stenosis (1-24%); the rest of the vessel is unremarkable. Branches AM, R-PDA, R-PLB: no plaque.
Also seen as:segment-involvement score, segmental involvement score
The SIS counts coronary segments with plaque, of any composition and with any degree of stenosis: each segment with plaque scores 1 point. CAD-RADS 2.0 calculates it over 16 segments, without listing them, with a maximum of 16, and SCCT 2026 keeps that maximum although its model has 18 segments. It is more reproducible than visual estimation of burden.
Source: SCCT 2026, section on plaque volume, p. 6 · “A score of 1 is given for each segment with plaque, with the highest possible score of 16.”
Details
In practice. Go through the coronary tree segment by segment and count each one that has plaque, even if minimal. If plaque sits at the junction of two segments, including bifurcations, it is assigned to the preceding segment. Example with codominance and a ramus intermedius: a plaque that starts in the LM and continues into the proximal LAD scores 2 points; two separate plaques in the mid LAD score 1; and one plaque in the ramus intermedius, another in the R-PDA and another in the L-PDA score 3. The SIS is 6, which corresponds to P3. If there is also plaque in the acute marginal branch, which Table 1 of SCCT 2026 does not number, the map counts it and the SIS is 7, still P3. A reader who does not count it gets one point less, and at the boundary between two bands, for example from 5 to 4 segments, that point changes P.
Pitfall. Counting plaques instead of segments is an error. A long plaque in the proximal and mid LAD scores 2 points, and three plaques in one segment score 1.
Other sources. Some studies call disease with plaque in more than 4 segments "extensive". The glossary follows CAD-RADS 2.0, in which 5 to 7 segments correspond to P3 (severe) and only 8 or more to P4 (extensive). (Bittencourt 2014; SCCT 2026, Table 3)
How the map counts the SIS. Each segment present on the map that has plaque scores 1 point, whether it has one plaque or several and whatever its grade; a segment marked “N” does not count. The last column separates what the guidelines set from what is a map convention.
Map segment
Number in SCCT 2026
When it scores 1 point on the map
Origin of the rule
Left main (LM)
5
If it has plaque. With an anatomy without a left main, chosen in “Coronary artery origins”, it is removed from the map and does not count
SCCT 2026
LAD proximal, LAD mid and LAD distal
6, 7 and 8
If it has plaque
SCCT 2026
1st Diagonal (D1) and 2nd Diagonal (D2)
9 and 10
If it has plaque
SCCT 2026
Ramus intermedius (RI)
17
If it has plaque and the ramus is present. With “Ramus intermedius absent”, or without a left main, its plaque is kept but does not count
SCCT 2026
LCx proximal and LCx distal
11 and 13 (Table 1 calls 13 distal)
If it has plaque
SCCT 2026
1st Obtuse marginal (OM1) and 2nd Obtuse marginal (OM2)
12 and 14
If it has plaque
SCCT 2026
RCA proximal, RCA mid and RCA distal
1, 2 and 3
If it has plaque
SCCT 2026
Acute marginal (AM)
No number
If it has plaque, with any dominance
Map convention: SCCT 2026 describes it in the text but does not number it or say whether it counts
Right PDA (R-PDA) and Right posterolateral (R-PLB)
4 and 16
If it has plaque and dominance is “Right” or “Balanced”
The R-PDA follows the SCCT 2026 definition of dominance; that the R-PLB exists only with those dominances is a map convention
Left PDA (L-PDA) and Left posterolateral (L-PLB)
15 and 18
If it has plaque; the L-PDA only with dominance “Left” or “Balanced”
The L-PDA follows the SCCT 2026 definition of dominance; the L-PLB is on the map with all three dominances, as in Table 1
Total
Maximum 16
Adds the segments with plaque and caps the total at 16. With a ramus intermedius, the map has 17 segments with right or left dominance and 19 with codominance. The cap never changes P: from 8 segments it is already P4
The maximum comes from SCCT 2026 and CAD-RADS 2.0; applying it as a cap over 17 or 19 segments is a map convention
Source: SCCT 2026, Table 1, p. 7, and text, pp. 4–5 and 6; CAD-RADS 2.0, section 3.2.1. The third column describes the map, verified on 2026-10-09.
In CCTA Map
In the “Plaque burden (P)” section of “Modifiers P · I ▾”, “Auto (map)” mode counts the segments present on the map that have plaque and converts the total to P1–P4; the panel shows it, for example, as “SIS 3 segments → P2”, and the template prints “Plaque burden: moderate (P2; SIS 3).” Several plaques in one segment score 1, and a plaque drawn with a single stroke across two segments counts in both. The table under “Details” shows which segments count and which of these rules are map conventions. A segment with a stent without restenosis and no other plaque does not count; neither SCCT 2026 nor CAD-RADS 2.0 says whether it should. Each graft with a stenosis also counts, and the report says so with “bypass grafts included”. Plaque set aside by N does not count.
Literal output of the map's template
Plaque burden: moderate (P2; SIS 3).
Left anterior descending (LAD): proximal segment: non-calcified plaque causing mild stenosis (25-49%); mid segment: non-calcified plaque resulting in mild stenosis (25-49%); the remainder is unremarkable. Branches D1, D2: no plaque.
Right coronary (RCA): mid segment: calcified plaque producing minimal stenosis (1-24%); the rest of the vessel is unremarkable. Branches AM, R-PDA, R-PLB: no plaque.
Figure 5. SIS counter. Tap each segment that has plaque, of any composition or grade; the counter adds one point per segment and shows the corresponding plaque burden category. Tap a segment again to remove it.
Also seen as:Agatston calcium score, calcium scorenot recommended, CAC scorenot recommended, coronary artery calcium scorenot recommended, CACS(the SCCT 2023 terminology, Table 4, prefers “Agatston score”; CAD-RADS 2.0 and SCCT 2026 still write “calcium score”)not recommended, CAC-DRS(SCCT reporting system from 2018, with categories A0–A3 and the number of arteries with calcium)
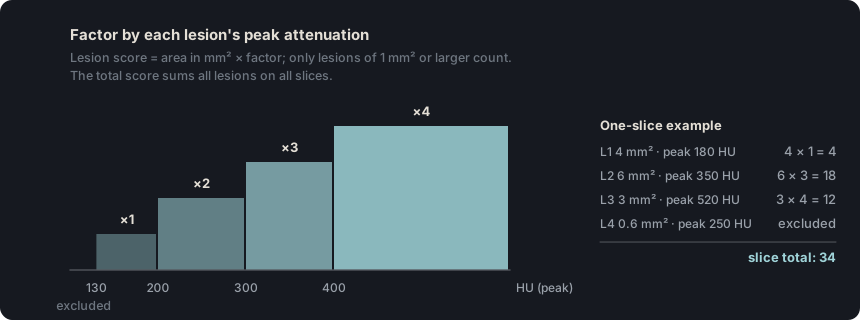
For each coronary lesion, the area of calcium above the 130 HU threshold is multiplied by a factor of 1 to 4 according to its peak attenuation. The score is the sum of these products.
How to write it
Agatston score of 0 on the non-contrast acquisition.
Do not confuse: An Agatston score of 0 means that no coronary calcium was detected, not that there is no atherosclerosis: CAD-RADS 0 requires no plaque, calcified or non-calcified, and no stenosis on CCTA.
Source: Neves PO, et al. Radiol Bras 2017 (review), section "Agatston method" · “The Agatston method uses the weighted sum of lesions with a density above 130 HU, multiplying the area of calcium by a factor related to maximum plaque attenuation”
Details
In practice. It is calculated on the non-contrast ECG-gated acquisition, before the angiogram, with the standard protocol of 120 kVp and 3 mm slices. If performed, the total is reported and can be used to assign plaque burden.
Pitfall. The Agatston score measures only calcified plaque. CAD-RADS 2.0 asks that it be combined with at least a qualitative assessment of total plaque burden: P stays the same if there is no non-calcified plaque and may increase if there is; with a score of 0 and visible plaque, P is assigned with the SIS or visual assessment.
Other sources. The SCCT CAC-DRS (2018) groups the score into A0 (0), A1 (1–99), A2 (100–299) and A3 (300 or more), and adds the number of arteries with calcium (for example, A2/N3). Its cutoffs differ slightly from those of P1–P4. The SCCT 2023 terminology recommends the name “Agatston score” rather than “calcium score” or “CAC score”, and defines calcium volume and calcium mass separately. (CAC-DRS, Hecht 2018; Obisesan 2021; SCCT 2026, Table 3; SCCT 2023 terminology, Table 4)
In CCTA Map
In “Calcium (Agatston)” mode you enter the value and the map converts it to P1–P4; the panel shows, for example, “Agatston 260 → P2”, and the template prints “Plaque burden: moderate (P2; Agatston 260).” The field accepts a period or a comma. If exactly three digits follow the separator, it is read as a thousands separator: “1,250” or “1.250” is 1250 (P4). Otherwise it is read as a decimal separator and the rounded whole number is used: “87.3” or “87,3” is 87 (P1). If no plaque is drawn on the map, a value greater than 0 gives CAD-RADS 1 with that P, as in “CAD-RADS 1/P2” with an Agatston score of 120, and vessels without findings are written as “no stenosis”, not as “no atherosclerotic disease”. That per-vessel wording belongs to the normal template, which the map applies by default. With Agatston 0 and plaque on the map, P comes from the SIS, with the note “P by SIS (Agatston 0 does not reflect non-calcified plaque)” in the P panel; the report says only “(P by SIS)”. With a value above 0, this mode uses only the score even if the map’s SIS gives a higher band: CAD-RADS 2.0 points both ways, and the decision is still pending with the author, with no warning on the map.
Figure 6. The Agatston score multiplies the area of each lesion by a factor that depends on its peak attenuation and sums the results for all lesions on all slices.
Self-assessment
Short questions to check the key points. The answer appears once you choose an option.
1A continuous plaque runs through the proximal, mid and distal RCA. There is also a plaque in the proximal LAD and another in the proximal LCx, and no other plaque. What is the SIS and what plaque burden does it indicate?
The SIS counts segments, not plaques. The continuous plaque scores 3 points, one for each RCA segment; with the proximal LAD and proximal LCx the total is 5, which corresponds to P3. See the term
2In the proximal LAD there is a plaque with positive remodeling and no other feature. In the mid LAD, separate from the first, another non-calcified plaque has an internal attenuation of 20 HU and no other feature. How is this reflected in the CAD-RADS category?
The modifier requires two or more features in the same plaque. Here each plaque has one: the features are described in the findings, but the category does not carry /HRP. See the term
3The Agatston score is 0. On CTA there is non-calcified plaque in the proximal LAD, mid LAD, proximal LCx and proximal RCA, with no stenosis of 50% or more, and no other plaque. What plaque burden is assigned?
When methods disagree, the more severe assessment is used. The Agatston score does not measure non-calcified plaque; the SIS is 4, which corresponds to P2. See the term
4In the proximal LAD, the outer vessel diameter at the plaque is 4.0 mm and the lumen diameter is 2.6 mm. The outer reference diameters are 3.9 mm in the healthy proximal segment and 3.1 mm in the distal segment. What is the remodeling index?
Divide the outer diameter at the lesion by the mean of the references: 4.0 / 3.5 = 1.14, greater than 1.1. Using only the proximal reference gives 1.03, and using the lumen gives 0.74. See the term
5On the cross-section of a proximal RCA plaque there is a large low-attenuation center in contact with the lumen, surrounded by a thin, continuous ring of dense calcium. How is it described?
In the napkin-ring sign, the ring is non-calcified plaque tissue denser than the center, and CAD-RADS 2.0 defines it in a non-calcified plaque. A ring of dense calcium does not meet the criterion and, together with the non-calcified center, makes the plaque partially calcified. See the term
6On the non-contrast phase, the only coronary calcium deposit is in the proximal LAD and appears on a single slice: it measures 5 mm² and its peak attenuation is 320 HU. CTA shows no other plaque. What is the Agatston score and what plaque burden does it indicate?
The factor depends on the lesion's peak attenuation: 300 to 399 HU gives 3, so the score is 5 × 3 = 15. A value of 1 to 100 corresponds to P1, as does an SIS of 1. See the term
Rajiah PS, Alkadhi H, Andreini D, Bullock-Palmer RP, Chinnaiyan K, Chow B, et al. Interpretation and reporting of coronary computed tomographic angiography (2026 update): an expert consensus document of the Society of Cardiovascular Computed Tomography (SCCT). J Cardiovasc Comput Tomogr. 2026. doi:10.1016/j.jcct.2026.08.014 Version of record published online in September 2026 under CC BY 4.0, not yet assigned to an issue; cited pages refer to the PDF of this published version.
Cury RC, Leipsic J, Abbara S, Achenbach S, Berman D, Bittencourt M, et al. CAD-RADS 2.0 - 2022 Coronary Artery Disease-Reporting and Data System: an expert consensus document of the SCCT, ACC, ACR and NASCI. J Cardiovasc Comput Tomogr. 2022;16(6):536-57. doi:10.1016/j.jcct.2022.07.002
Koweek L, Achenbach S, Berman DS, Carr JJ, Cury RC, Ghoshhajra B, et al. Standardized medical terminology for cardiac computed tomography 2023 update: an expert consensus document of the SCCT, AAPM, ACR, NASCI and RSNA. J Cardiovasc Comput Tomogr. 2023;17(5):345-54. doi:10.1016/j.jcct.2023.06.002
Narula J, Chandrashekhar Y, Ahmadi A, Abbara S, Berman DS, Blankstein R, et al. SCCT 2021 expert consensus document on coronary computed tomographic angiography: a report of the Society of Cardiovascular Computed Tomography. J Cardiovasc Comput Tomogr. 2021;15(3):192-217. doi:10.1016/j.jcct.2020.11.001
Neves PO, Andrade J, Monção H. Coronary artery calcium score: current status. Radiol Bras. 2017;50(3):182-9.
Tamburino C, Tomasello SD, Capodanno D, Di Salvo ME, Marzà F, Galassi AR. Long-term follow-up after drug eluting stent implantation in left main trifurcations. EuroIntervention. 2009;5(4):432-7. doi:10.4244/eijv5i4a68
Kovacevic M, Burzotta F, Elharty S, Besis G, Aurigemma C, Romagnoli E, et al. Left main trifurcation and its percutaneous treatment: what is known so far? Circ Cardiovasc Interv. 2021;14(3):e009872. doi:10.1161/CIRCINTERVENTIONS.120.009872
Kim C, Park CH, Lee BY, et al. 2024 consensus statement on coronary stenosis and plaque evaluation in CT angiography from the Asian Society of Cardiovascular Imaging-Practical Tutorial (ASCI-PT). Korean J Radiol. 2024;25(4):331-42. doi:10.3348/kjr.2024.0112
Sources for the “Other sources” notes
Leipsic J, Abbara S, Achenbach S, Cury R, Earls JP, Mancini GBJ, et al. SCCT guidelines for the interpretation and reporting of coronary CT angiography: a report of the Society of Cardiovascular Computed Tomography Guidelines Committee. J Cardiovasc Comput Tomogr. 2014;8(5):342-58. doi:10.1016/j.jcct.2014.07.003
Cury RC, Abbara S, Achenbach S, et al. CAD-RADS: Coronary Artery Disease – Reporting and Data System. J Cardiovasc Comput Tomogr. 2016;10(4):269-81. doi:10.1016/j.jcct.2016.04.005
Nieman K, García-García HM, Hideo-Kajita A, et al. Standards for quantitative assessments by coronary computed tomography angiography (CCTA): an expert consensus document of the SCCT. J Cardiovasc Comput Tomogr. 2024;18(5):429-43. doi:10.1016/j.jcct.2024.05.232
Williams MC, Moss AJ, Dweck M, et al. Coronary artery plaque characteristics associated with adverse outcomes in the SCOT-HEART study. J Am Coll Cardiol. 2019;73(3):291-301. doi:10.1016/j.jacc.2018.10.066
van Rosendael SE, Shiyovich A, Cardoso RN, Souza Freire CV, van Rosendael AR, Lin FY, et al. The role of cardiac computed tomography angiography in risk stratification for coronary artery disease. J Soc Cardiovasc Angiogr Interv. 2024;3(11):102230. doi:10.1016/j.jscai.2024.102230
Yang S, Lee JM, Hoshino M, Murai T, Choi KH, Hwang D, et al. Prognostic implications of comprehensive whole vessel plaque quantification using coronary computed tomography angiography. JACC Asia. 2021;1(1):37-48. doi:10.1016/j.jacasi.2021.05.003
Pozo E, Agudo-Quilez P, Rojas-González A, Alvarado T, Olivera MJ, Jiménez-Borreguero LJ, et al. Noninvasive diagnosis of vulnerable coronary plaque. World J Cardiol. 2016;8(9):520-33. doi:10.4330/wjc.v8.i9.520
Bittencourt MS, Hulten E, Ghoshhajra B, et al. Prognostic value of nonobstructive and obstructive coronary artery disease detected by coronary computed tomography angiography to identify cardiovascular events. Circ Cardiovasc Imaging. 2014;7(2):282-91. doi:10.1161/CIRCIMAGING.113.001047
Hecht HS, Blaha MJ, Kazerooni EA, et al. CAC-DRS: Coronary Artery Calcium Data and Reporting System. An expert consensus document of the Society of Cardiovascular Computed Tomography (SCCT). J Cardiovasc Comput Tomogr. 2018;12(3):185-91. doi:10.1016/j.jcct.2018.03.008
Obisesan OH, Osei AD, Uddin SMI, Dzaye O, Blaha MJ. An update on coronary artery calcium interpretation at chest and cardiac CT. Radiol Cardiothorac Imaging. 2021;3(1):e200484. doi:10.1148/ryct.2021200484
This glossary translates and adapts definitions, tables and figures from the SCCT 2026 consensus: Rajiah PS, et al. Interpretation and reporting of coronary computed tomographic angiography (2026 update): an expert consensus document of the Society of Cardiovascular Computed Tomography (SCCT). J Cardiovasc Comput Tomogr. 2026. doi:10.1016/j.jcct.2026.08.014, published under the CC BY 4.0 license. Changes: plain-language rewording and reorganized tables; the diagrams are dynamic schematics of the map and do not reproduce the guideline figures exactly. The SCCT has not reviewed or endorsed this glossary. CC BY 4.0